
Depression and the Nervous System: When Depression Feels Like Shutdown

Depression is often described in terms of mood.
We associate it with sadness, hopelessness, negative thinking and a loss of enjoyment in life. These can certainly be part of depression, but they do not describe everyone’s experience.
For some people, depression feels less like intense sadness and more like shutdown.
They may feel physically heavy, exhausted or emotionally numb. Motivation disappears. Things they previously cared about no longer seem important. Social interaction becomes difficult. Even relatively simple activities can feel as though they require enormous effort.
A person may describe feeling as though they have simply “switched off.”
Understanding what is happening in the nervous system can give us another way of thinking about these experiences.
It is important, however, not to oversimplify this. Depression is complex. There is no single nervous-system state that explains every case of depression, and depression should not simply be equated with “shutdown.”
What we can say is that our psychological and physiological states are deeply interconnected.
Depression Is More Than a Thought Pattern
Psychological approaches have traditionally placed considerable emphasis on thoughts, beliefs and behaviour.
These are important.
However, human experience does not take place solely within our conscious thinking.
Our brain and body are constantly monitoring and responding to information from both our internal and external environments.
The autonomic nervous system helps regulate many processes that occur largely outside conscious control, including heart rate, breathing, digestion and aspects of our response to stress.
The endocrine and immune systems are also involved.
Consequently, when somebody experiences prolonged stress, overwhelming events or persistent perceptions of threat, the effects can extend far beyond their conscious thoughts.
Their whole physiological state can change.
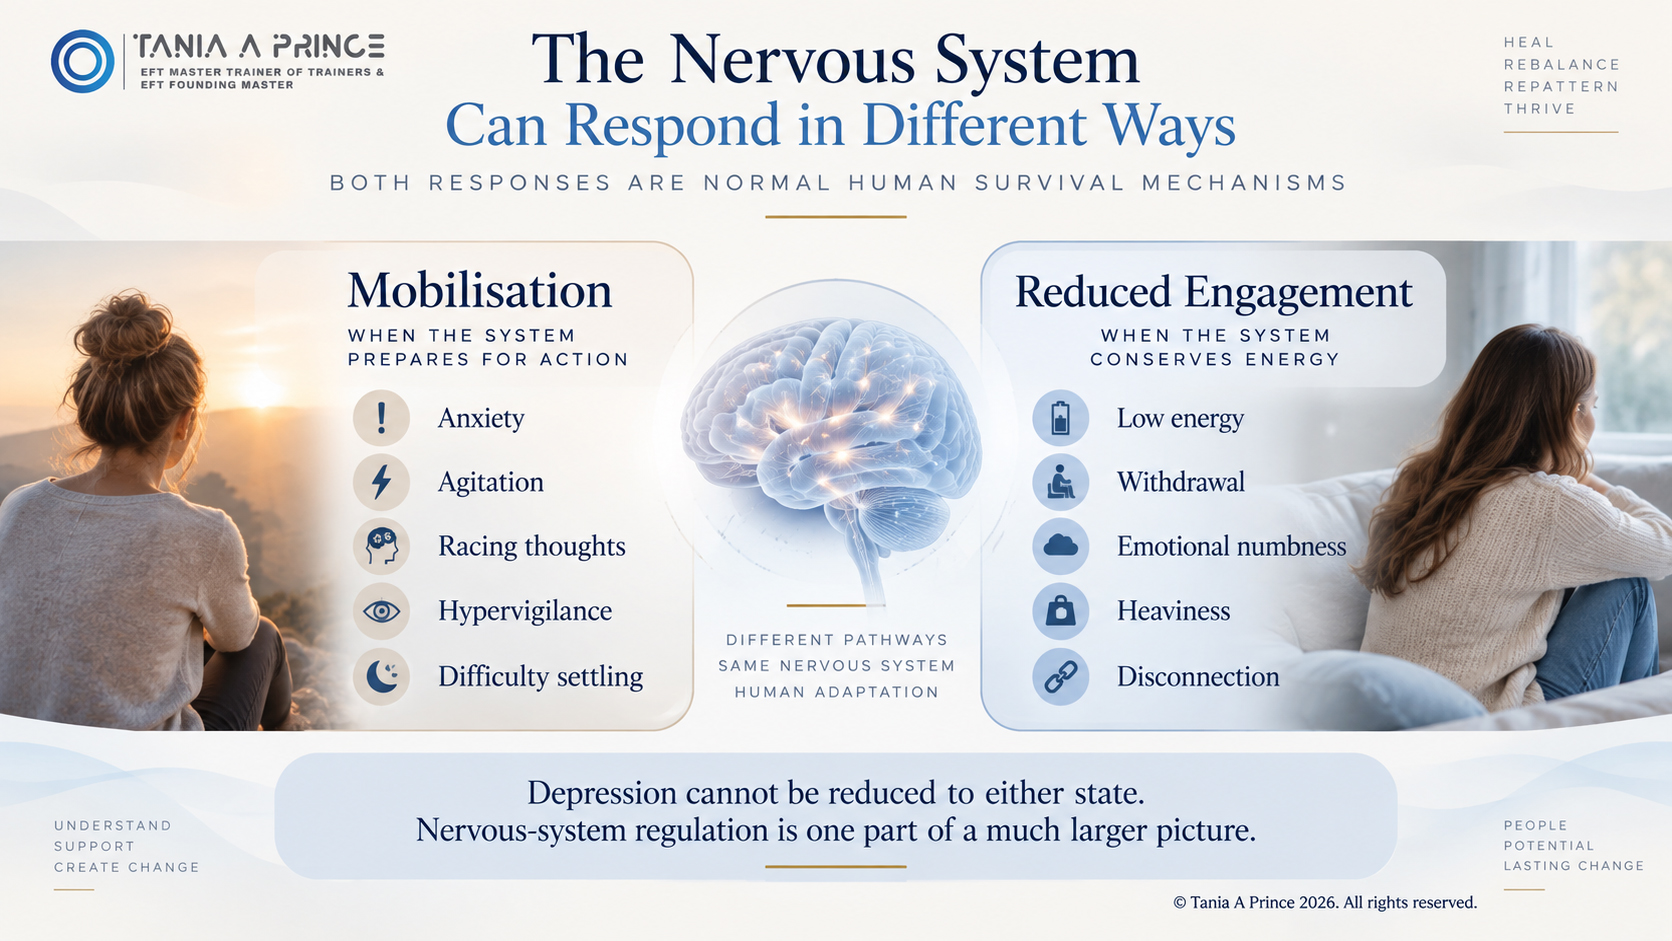
Mobilisation: When the System Prepares for Action
When threat is detected, one possible response is mobilisation.
The sympathetic nervous system becomes more active and prepares the body for action.
Depending upon the circumstances, a person may experience increased heart rate, muscular tension, heightened alertness, agitation, rapid thoughts or difficulty settling.
Psychologically, this can appear as anxiety, irritability or hypervigilance.
The person may feel constantly “on.”
This is commonly associated with the familiar fight-or-flight response.
However, mobilisation is not the only possible response to overwhelming circumstances.
When Mobilisation Gives Way to Reduced Engagement
There are situations in which fighting or escaping is not possible.
There are also circumstances in which stress is prolonged and there appears to be no effective action a person can take to resolve it.
People can then experience very different patterns of response, including immobility, withdrawal, reduced engagement, emotional numbing or dissociation.
Subjectively, this can feel very different from anxiety.
Rather than:
“I need to get away.”
the experience may be closer to:
“I can’t do anything.”
Rather than racing thoughts, there may be difficulty thinking.
Rather than feeling intensely emotional, the person may struggle to feel very much at all.
Rather than wanting to escape, they may want to withdraw from the world.
Some of these experiences can also occur in depression.
That does not mean depression is a shutdown response. It means that some depressive presentations include changes in arousal, motivation, energy and engagement that can usefully be considered alongside nervous-system regulation.
Is Depression a “Dorsal Vagal Shutdown”?
The term dorsal vagal shutdown has become increasingly common in discussions about trauma and mental health.
It is sometimes used to explain depression, emotional numbness, exhaustion and dissociation.
We need to be cautious about this.
The autonomic nervous system is undoubtedly involved in stress regulation, and research has identified autonomic differences associated with depression. However, reducing a complex condition such as depression to activity in one branch of the vagus nerve goes beyond what the scientific evidence currently supports.
It is therefore more accurate to say that some people experiencing depression show patterns of reduced activation, withdrawal and autonomic dysregulation that may form part of a much larger biological and psychological picture.
That distinction matters.
Could Withdrawal Initially Be Protective?
When we examine human behaviour through the lens of survival, some responses that appear problematic in everyday life begin to make more sense.
Mobilisation requires energy.
If an organism is injured, ill, overwhelmed or unable to change its circumstances, reducing activity can sometimes have protective value.
We see something similar when we become physically ill.
During an infection, immune signalling can contribute to what researchers call sickness behaviour.
A person may become tired, sleep more, lose motivation, withdraw socially and lose interest in normal activities.
These behaviours encourage rest and conservation of energy while the body deals with illness.
Interestingly, researchers are also investigating inflammatory processes in depression.
Some people with depression show evidence of increased inflammatory activity, although this is not true of everyone with depression and does not mean that depression is simply an inflammatory illness.
It does demonstrate something important:
mood, motivation, immunity, energy and behaviour are not separate systems.
They continually influence one another.
Trauma, Stress and the Nervous System
Trauma can add another dimension.
During an overwhelming event, a person’s nervous system may initially mobilise.
There may be a strong urge to fight, escape or take action.
If effective action is impossible, other defensive responses can occur, including immobility, freezing, dissociation or reduced engagement.
The event may subsequently be over, but the nervous system can continue responding to cues associated with what happened.
These cues do not necessarily need to be consciously recognised.
A facial expression, tone of voice, smell, place, physical sensation or interpersonal situation can potentially activate learned associations.
The person may therefore experience a sudden change of state without consciously understanding why.
This does not mean that unexplained depression is always caused by trauma.
Depression can have many contributing factors, including genetics, physical illness, hormonal changes, medication, sleep disturbance, chronic stress, difficult life circumstances, substance use and nutritional or metabolic factors.
For some people, however, trauma and unresolved stress may form part of the picture.
Depression and the Gut–Brain Connection
The nervous system does not operate independently from the rest of the body.
One particularly interesting area of research concerns the gut–brain axis.
The brain and gastrointestinal system communicate bidirectionally through several pathways, including the autonomic nervous system, vagus nerve, immune signalling, endocrine systems and substances produced or influenced by the gut microbiome.
Chronic stress can affect gastrointestinal function.
It can influence intestinal movement, appetite, digestion, immune activity and the environment in which intestinal microorganisms live.
At the same time, signals originating within the gut can influence the nervous system and brain.
Researchers are investigating relationships between depression and changes in the gut microbiome, inflammation and tryptophan metabolism.
This does not mean that an unhealthy gut simply “causes depression.”
The relationship is much more complex.
Depression itself can alter sleep, eating, physical activity and stress physiology, all of which can subsequently affect gut health.
It is therefore better understood as a feedback system.
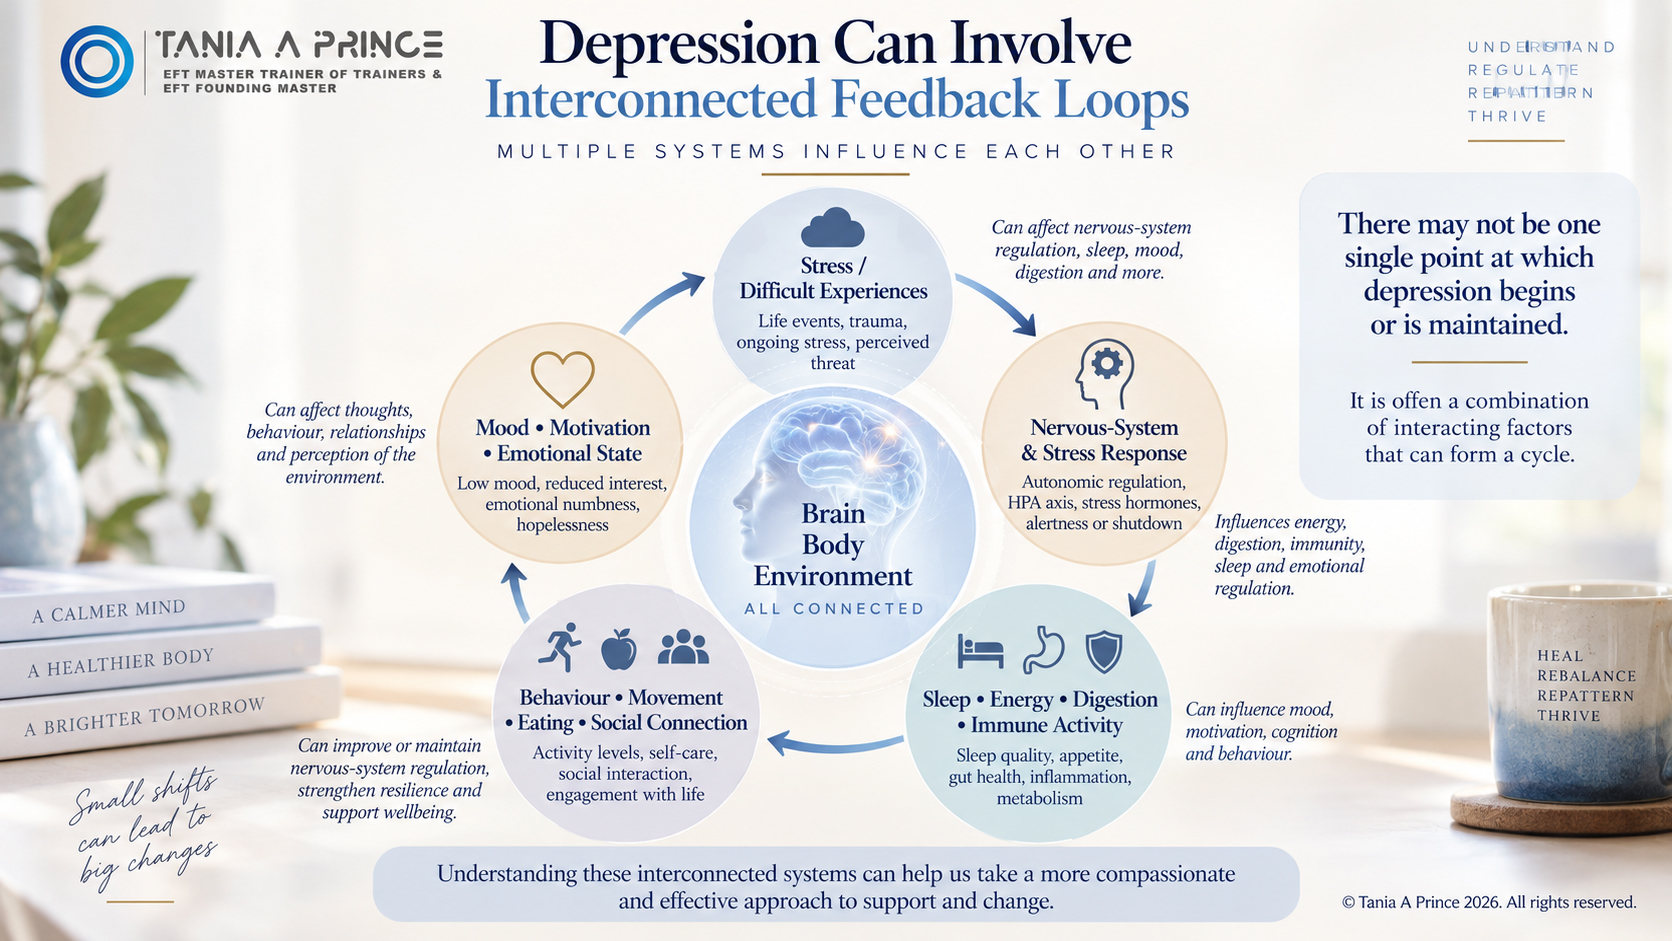
Depression May Involve Multiple Feedback Loops
One of the limitations of searching for a single cause of depression is that, once a problem becomes established, several systems may begin maintaining one another.
For example, prolonged stress may affect sleep.
Poor sleep can affect emotional regulation and energy.
Reduced energy can lead to less movement and social interaction.
Changes in activity and eating can affect metabolic and gastrointestinal health.
Inflammatory and metabolic changes may influence brain function.
Low mood can then further reduce activity, sleep quality and self-care.
The original problem is no longer necessarily the only thing maintaining the current state.
A feedback loop has developed.
This is why it can be useful to think about the person as an interconnected system rather than attempting to locate depression exclusively within either the mind or the body.
Why “Think Positive” Can Be Such an Unhelpful Message
If somebody is experiencing profound emotional and physiological withdrawal, asking them simply to think positively can create an enormous mismatch with their current state.
They may know intellectually that their life contains positive things.
That does not necessarily mean they can access the corresponding emotional or physiological state.
For someone who feels profoundly numb or shut down, the immediate goal may not need to be happiness.
A much smaller shift may be significant.
For example:
numbness → noticing sensation → greater connection → increased capacity for engagement → interest → pleasure
Change does not always need to occur in one enormous leap.
Sometimes the nervous system needs opportunities to experience manageable shifts in state.
A Different Question to Ask
Instead of asking only:
“What is this person thinking?”
we might also ask:
“What state is this person in?”
Are they highly activated and anxious?
Are they exhausted and withdrawn?
Do they feel emotionally numb?
Are they dissociating?
Can they comfortably feel sensations within their body?
Can they experience safety or connection?
What happens physiologically when they begin talking about a particular person, situation or memory?
These questions do not replace psychological assessment.
They add another layer to it.
The MBIR™️ Perspective
In Mindfulness-Based Inner RePatterning™️ (MBIR™️), we work with the person’s present experience rather than assuming in advance what is causing it.
That distinction is important.
If somebody appears withdrawn or shut down, we do not need to impose the interpretation that their nervous system is protecting them, that trauma must be present, or that a particular “part” is responsible.
We can become curious about what is actually happening.
MBIR™️ incorporates approaches for working with state, internal experience, resources and patterns that may be maintaining a person’s response.
The Safe State can provide an important resource within this work.
Where appropriate, Parts work can also explore whether some aspect of the person has concerns or objections about change. A protective function should not simply be assumed; it can be discovered through the person’s own experience.
The aim is not necessarily to force somebody from a low state into a highly positive one.
A small increase in regulation, awareness, connection or capacity may represent meaningful movement.
Depression Is Not Simply “All in the Mind”
Perhaps one of the most important developments in our understanding of mental health is recognition of how difficult it is to separate mind from body.
Our experiences influence our physiology.
Our physiology influences our experience.
The brain communicates with the gut.
The gut communicates with the brain.
The nervous, endocrine and immune systems continually interact.
Our relationships and environment influence all of them.
Depression therefore cannot always be adequately understood as either a problem with thinking or a problem with biology.
For many people, it may be more useful to consider the interaction between experience, brain, body, nervous-system state, behaviour and environment.
And sometimes, what looks from the outside like a lack of motivation may be something considerably more complex happening within the person.
Important: Depression can be a serious mental health condition. Persistent or severe depression, significant deterioration in functioning, or thoughts of suicide or self-harm require appropriate assessment and support from a qualified healthcare professional. Nervous-system approaches and complementary therapeutic techniques should not be used as substitutes for necessary medical or mental-health care.
©️ Tania A Prince 2026. All rights reserved.
